GLP-1 RAs vs MRAs: Resistant Hypertension with Obesity
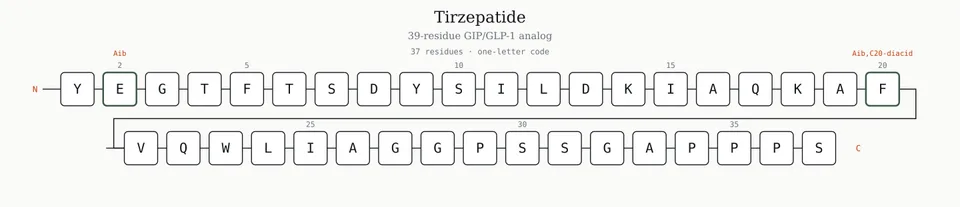
Resistant hypertension — blood pressure that remains uncontrolled despite three or more antihypertensive agents — is disproportionately common in individuals with overweight or obesity. The current guideline-recommended fourth-line therapy is a mineralocorticoid receptor antagonist (MRA). But a new retrospective cohort study published in EClinicalMedicine this month asks whether GLP-1 receptor agonists might offer a better alternative [PMID 42701458].
The study design
The analysis used the TriNetX US Collaborative Network, which aggregates electronic health record data from 67 healthcare organizations. The investigators identified 213,309 eligible adults with overweight or obesity and resistant hypertension who had been prescribed either a GLP-1 receptor agonist or an MRA as fourth-line therapy.
After propensity score matching to account for differences in age, sex, baseline blood pressure, comorbidities, and concurrent medications, 4,153 matched pairs remained for comparison. The median follow-up was 1.4 years.
The numbers
The primary composite outcome — major adverse cardiovascular events (MACE), defined as myocardial infarction, stroke, or cardiovascular death — occurred less frequently in the GLP-1 RA group:
- MACE: HR 0.63 (95% CI 0.52–0.78)
- All-cause mortality: HR 0.48 (95% CI 0.37–0.62)
- Composite kidney outcome (new-onset CKD, progression to ESRD, or acute kidney injury): HR 0.63 (95% CI 0.49–0.81)
Despite these lower cardiovascular and kidney event rates, GLP-1 RA therapy was associated with smaller reductions in blood pressure compared with MRA therapy — a finding the authors describe as “counterintuitive but consistent” with emerging evidence that GLP-1 receptor agonists may confer cardiovascular benefit through mechanisms beyond blood pressure lowering, including weight reduction, improved endothelial function, and anti-inflammatory effects.
Why this matters
Resistant hypertension in patients with obesity is a common clinical scenario with limited evidence to guide fourth-line drug selection. The standard approach — adding an MRA — is effective for blood pressure reduction but may not address the broader cardiometabolic risk profile of this population. GLP-1 receptor agonists, which simultaneously reduce weight, improve glycemic control, and demonstrate anti-inflammatory effects, may address multiple drivers of cardiovascular risk in a single therapeutic class.
The study’s effect estimates are large enough to warrant attention: a 37 percent lower hazard of MACE and a 52 percent lower hazard of all-cause mortality are substantial, even acknowledging the limitations of retrospective data.
Caveats
This is an observational study, not a randomized trial. Propensity score matching reduces confounding by measured variables but cannot eliminate unmeasured confounding — patients selected for GLP-1 RA therapy may differ systematically from those selected for MRA therapy in ways the data cannot capture. The short follow-up (median 1.4 years) means durability of the observed effects is unknown. And the study reports association, not causation.
That said, studies of this scale — drawn from 67 healthcare organizations with over 200,000 screened patients — provide a useful signal, particularly in a clinical area where randomized evidence is limited. The authors note that a dedicated randomized trial would be the appropriate next step.
The broader picture
For readers interested in the fuller reference data on the GLP-1 receptor agonists used in this cohort — primarily tirzepatide and semaglutide — the Research Protocols reference archive maintains detailed monographs with pharmacokinetic data and trial registrations. Certificate of analysis data on indexed compounds, including batch-level purity and method reporting, is available through CertIQX.